These “readiness scores” as a composite of multiple metrics, with heart rate variability (HRV) being front and center for most.
In this edition of Ground Truths I am going to review what we know about heart rate variability and readiness scores.
Heart Rate VariabilityHRV is the variation in normal heart cycle timing.
Distinct from heart rate, individuals with the same heart rate can have very different HRVs.
At that time many subscribers asked me to cover heart rate variability, which I finally got to here.
On September 9th, Apple announced it was revamping its Apple Watch Health Sensing System, rolling out a Readiness score (0 to 10), and increasing the frequency of heart rate variability (HRV) outputs 24-fold. This can be viewed as upping its competition with various other consumer wearable sensors. These “readiness scores” as a composite of multiple metrics, with heart rate variability (HRV) being front and center for most. The majority of Americans are now using wearable sensors, which equates to well over 100 million adults. HRV and Readiness scores are increasingly being marketed as a measurement of autonomic nervous system health, a digital marker for future disease, a clock for biological age, and a holistic metric to promote healthspan and even longevity. (Apple also introduced a new longevity tab and “Health Age”.) None of this has been proven. In this edition of Ground Truths I am going to review what we know about heart rate variability and readiness scores.
Heart Rate Variability
HRV is the variation in normal heart cycle timing. The variability of the heart rate, the barely perceptible millisecond changes in time between consecutive heart beats (see R-R intervals in the Figure below, left panel), is due to interplay between the sympathetic and parasympathetic (vagal nerve) inputs. Distinct from heart rate, individuals with the same heart rate can have very different HRVs. It is a rough reflection of the autonomic nervous system (ANS) activity, inadequate to say whether a person’s ANS function is abnormal. For more than three decades, heart rate variability (HRV) has been measured and several studies have found an association of low HRV and clinical outcomes, particularly a link with higher all-cause and cardiovascular mortality. There have also been less well established links of low HRV to risk of early cognitive impairment, dementia, mental illness, Type 2 diabetes and substance abuse. An important reminder is that HRV is a surrogate marker without any established cause-and-effect relationship. If you increase your HRV, that doesn’t mean it will improve health outcomes. In fact, there is no hard evidence for that.
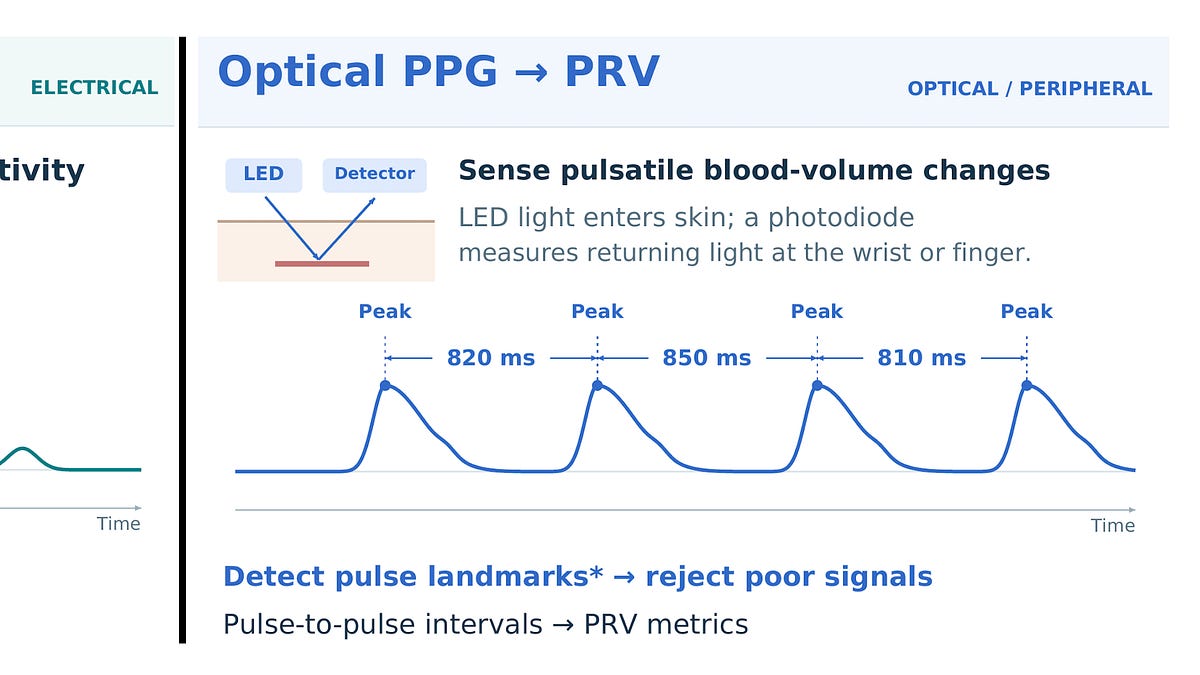
All that work linking to health outcomes was done with electrocardiogram (ECG) derived HRV. Now, in the era of consumer wearables, this is getting assessed differently, by optical pulse (yes, the lights you see) plethysmography (PPG) or what is called pulse rate variability (PRV). They are not the same, as shown below (right panel) and only concordant when the delay between the ECG and pulse is kept constant, which basically means at rest. I should mention there’s also what I will call MPV, a mattress mechanical movement sensor, a derived heart rate variability, that companies like Eight Sleep use, even further away from directly measuring HRV.
HRV has not one uniform measurement but many different types of quantification, such as RMSSD, the magnitude of difference between successive R-R intervals of normal sinus beats (N-N) or SDNN, the standard deviation of NN intervals, both in milliseconds. SDNN is one of the so-called frequency domain HRVs (others are LF, HF, LF/HF). Different wearable sensors use different metics; Apple has relied on SDNN and nearly all of the others use RMSSD, which is generally considered the more accurate metric. There’s also the different length of time measured, such as for a matter of minutes, all day, or an overnight’s sleep. Short measurements are especially problematic since they don’t capture enough of respiratory modulation and other factors that influence HRV.
Share Ground Truths
How well does HRV correlate with PRV?
There are very limited studies, especially independently done. One that is commonly cited was conducted by Air Force researchers in only 13 healthy adults assessing Oura ring 3 and 4, Whoop 4.0, and Garmin Fenix 6 and showed a correlation coefficient of 0.88 to 0.97 and a mean absolute percentage error from 6 to 10%. The correlation is not a perfect 1.0, but there’s at least a fairly high level of correlation. HRV is supposed to increase during the night due to takeover of the parasympathetic nervous system, and higher during deep sleep.
A recent example of my 1 week, all day “HRV,” and one during sleep is shown below. As you can see, the N of 1 data are inconsistent for the same days from different sensors (Oura, AppleWatch, Fitbit Air, and Eight Sleep) by patterns, absolute numbers, and comparison with prior days and weeks.
The largest study in over 8 million Fitbit users (the old version, not Google Fitbit Air, introduced in May 2026) gives you a sense of the effect of age, sex, and the 2 different main HRV (here PRV) metrics, with RMSSD on the left and SDRR (=SDNN) on the right below.
That study, from data collected in 2018, is a major outlier, since all the more recent ones are tiny with respect to sample size. Many of the companies have not had independent evaluation of their HRV, such as Eight Sleep, but have published a low standard error on their website. There are some other published studies on the correlation between HRV and PRV, but they are all small and only in healthy adults. A scoping review emphasized the lack of study in underrepresented individuals, including the aged, people of color (which affects the PPG signal), and individuals who are underweight or obese. Add the typical adult age 60 plus with one or more chronic diseases. For example, one study in over 900 adults found poor correlation of HRV and PRV, non-uniformly underestimated across many chronic diseases (cardiovascular, endocrine, neurological, respiratory, and others), concluding PRV is “an invalid surrogate for HRV.” A recent systematic review of 43 studies comparing HRV and PRV found reasonable pooled absolute standardized error (HRV as gold standard) but only 10 of the studies provided quantitative synthesis in ideal conditions. Their main conclusion was similarly cautious: “PPG-derived HRV [PRV] should not be regarded as universally interchangeable with ECG-derived HRV across all devices, populations, and recording contexts.”
Factors Affecting HRV and PRV
That gets me to the long list of factors that affect HRV (and PRV) besides the device, the type of measurement (RMSSD, SDNN or others), the person’s signal, the sensor site, the duration of data capture, if weighting by sleep stage is used, how artifact is processed and corrected. And this list is not complete!:
Oura puts out data from their community of users (who input data) on what affects their overnight HRV. The factors currently provided are: no alcohol (increase 8%), melatonin (increase 2%, float tank (increase 2%), wine (decrease 4%), and party (decrease 14%) in overnight HRV. Must be some big parties!
What is a PRV measurement good for?
It has been falsely characterized as an index of “autonomic balance” and a specific indicator of stress. A 2018 review of the studies available for HRV and its relationship to stress, not using any of the current wearables, found that stress can lower HRV. But so can many other factors. The non-specificity of the signal, indexed to the table above, is striking.
Evidence from a UK Biobank study of over 46,000 participants with actual HRV looked at genetically predicted HRV, a genetic risk score, that failed to show the expected HRV-mortality link, indicating that HRV is likely not causal, but rather a reflection of person’s physiologic state.
A review of consumer wearable HRV data from 5 longitudinal studies showed that nighttime PRV was not associated with perceived stress, and surprisingly higher HRV, in the largest cohort (N=717 participants), was correlated with higher stress. An Oura ring cohort of 525 first-year college students found a link between overnight PRV and perceived stress, but that was also seen with resting heart rate, sleep, and respiratory rate.
Several very small studies have examined the relationship of HRV and athletic injuries or guiding training with mixed, and predominantly negative results. HRV biofeedback training with paced breathing had no significant effect on reducing stress or raising HRV, as demonstrated with sham controlled trials. When HRV for multiple days showed a decline in conjunction with body temperature, the Oura ring published data for prediction of Covid.
The WHOOP company sponsored an observational study, published in 2026, of 30,000 users for 72 weeks, without a control group, that reported reduced alcohol intake (5.8 % points) by self-report. That doesn’t tell us much, and particularly about the merits of HRV for behavioral change.
If you use the same device and conditions as longitudinal trends for multiple (at least 2-3) weeks that may be the one way to get something useful from the measurements. Data for overnight sleep with minimal motion and using RMSSD is the best proxy for real HRV. The reason to look at trends rather than any given night is that it more likely represents something, even though you won’t know with certainty what the “it” is. Keep in mind there are no data, no peer-reviewed evidence, to show that HRV fluctuation in-person has any correlation with health outcomes.
Share
Readiness Scores
These are proprietary scores that integrate different metrics for each of the wearables: no algorithms have been disclosed. They are unvalidated against health outcomes. In a review of 14 composite health scores of readiness and recovery, HRV contributed 86% to the scores, followed by reading heart rate (79%), physical activity and sleep duration (both at 71%). That review noted the substantial variability in measurement protocols and lack of standardization. Sleep staging is notoriously inconsistent and inaccurate by these sensors, which adds further to the HRV uncertainties for what the scores, which use sleep stage data, mean. Only resting heart rate has been shown consistently across devices to be extremely accurate.
I’ve made a Table to summarize what we know about which metrics are included, the scores, any peer-reviewed studies that compared the readiness score with health outcomes, and the corresponding (if any, NA-not available) citation. You will note that some companies do not use the term “readiness," such as WHOOP for recovery, and Garmin, which has 2 different scores, one of which is Body Battery. Eight Sleep uses the term “Fitness Score.” They all include HRV; Apple includes a new metric they call “Recovery HRV” which among other components uses 7-days of sleep, but it is unclear what this means or how it is differentiated from other scores (there are clearly no data for outcomes). We have no knowledge of how the different components are weighted or whether any of these scores are better than resting heart rate, HRV alone, physical activity, or any other single metric. Since none of these are standardized, they are not interchangeable, so if you get a 90 for Oura that has no relationship to a 90 on a Google Fitbit Air. Notably, the company can update its algorithm for readiness score at any point without notification to device users. Without any useful evidence of actionability for these scores or established relationship with health outcomes, it is hard to make a case for their value.
At the Apple recent announcement they showed their Readiness score (0-10) on the watch (Figure below) but there are no published data on this score, not even on their website. It’s available only on their new Watch Series 12 or Ultra 4 [of course, ;-)].
That exemplifies the problems with these scores, lack of data and evidence for being meaningful to promote health. Perhaps the best study (which isn’t saying much) is the WHOOP Recovery for golfer performance, because it did correlate with an objective outcome, even though there was no control group and the authors were all from the company. Among the 389 pro golfers, an absolute 10-per cent point increase in Recovery score was associated with about 0.5 fewer strokes per round. But that’s hardly a health outcome! WHOOP is also conducting a study in over 2,700 runners to see if their recovery score will be linked to less injuries and improved performance, but that is not yet published and has no control group or randomization.
Putting This in Context
For two decades I’ve been enthusiastic about the potential for digital health and particularly wearable biosensors. Over the years, we’ve seen some great progress for their ability to promote physical activity and accurately detect atrial fibrillation (the first FDA cleared deep learning AI for consumers). That work was the subject of rigorous research. But there are holes in the data and evidence for other metrics. One notable one is the “VO2 max” story that I wrote about earlier this year. At that time many subscribers asked me to cover heart rate variability, which I finally got to here.
When I dived into the research and publication for HRV and readiness scores, I expected to find at least some that were of high quality and demonstrated their utility by linkage to health outcomes. To my surprise, I found none.
The wearable sensor measurements for HRV (PRV) are, for the most part, accurate, but that validation work has only been done in small studies of healthy adults and does not take into account the long list of factors, from the device, software side, and the user side, that affect HRV measurements. Moreover, this metric chiefly relies on optical sensing and, as we have learned for heart rate PPG sensing, may be less accurate in people of color. Keep in mind that all of the health outcome association evidence comes from ECG-derived HRV; none are from wearable sensor data. I will repeat the key point: there's no peer-reviewed evidence to show that in-person HRV fluctuation—or efforts to raise your HRV— has any correlation with health outcomes. For those of you who look at your HRV on awakening, or even 2+ week trends of it being low, I hope this context helps to relieve any anxiety.
Yes, low HRV (not PRV) has been shown to increase risk of some diseases as summarized above. But efforts to raise your HRV—a surrogate metric— has not been established for improving any health outcomes. HRV does not have any evidence of causality (the genetic evidence actually goes against this possibility).
In this summary, I have not included data for other wearable sensors such as Polar, Samsung, Withings, Suunto, Amazfit, Coros, Ultrahuman, or additional mattress sensors. These are beyond my first-hand experience, and as far as I know from my in-depth review none have any peer-reviewed published data that differ from the 6 sensors I’ve reviewed here.
From the points I’ve gone over above, we’re not ready for readiness scores. Besides being proprietary, they are predominantly based on metrics that have their own issues. It’s compounding the problem, like building a house without a solid foundation that has never undergone a rigorous inspection, and then selling it. Like I mentioned for PRV, you can look at trends over weeks rather than any single day, to get a handle, but even that may not be helpful. There’s simply no evidence that these scores meaningfully relate to health outcomes. I’d emphasize they might, but that requires doing prospective or randomized studies to prove it. None exist.
There’s great promise for HRV/PRV utility. For example, Prof Maiken Nedergaard, who discovered the brain glymphatics that are essential in eliminating metabolic waste products from the brain during sleep, has posited that HRV could be a non-invasive marker for neuromodulator oscillations, brain-body regulatory circuits, and brain clearance. That would be extremely useful, but like everything else on HRV and readiness scores it requires solid research and validation.
The lay media isn’t helping much to get the story straight. Earlier this year The Economist published a piece entitled “The most useful indicator of your overall health” which ordained HRV as an “accumulated stress score.” That’s akin to the false assertion about VO2max: “V02 max is the singular most powerful marker for longevity.” As I’ve summarized here, that is not established. The fact is that so many things can lower HRV, including physical exercise (especially an intense workout), reduced sleep quality, stress, the list above, no less the device, signal, and software. Whatever fluctuations observed have not been correlated with any health outcome. Sadly, “datamaxxers” are widely using HRV and readiness scores that have never been validated to mean anything.
We already know that for some people using the sensors for sleep metrics, it can induce “orthosomnia,” an obsession to get high sleep quality, with associated high levels of anxiety. In an experiment done by a company to promote sleep quality for its employees, “For those employees who did use the trackers, many reported feeling perfectly rested until their tracker told them they had had a terrible night. Others were told that they had slept like a baby when they had actually been lying awake worrying about the quality of their sleep. “
The same problem can result from preoccupation with HRV or readiness scores, with anxiety that would lead to further reduction in both. It you are using a wearable like >100 million American adults, it’s OK to look at these data, but contextualized with the major caveats reviewed here. If you are one to require evidence that HRV or readiness scores are linked to health outcomes, you may not even want to look. The companies make it hard to turn them off!
Let me end with the companies that make and sell wearables. Apple’s doubling down on HRV (24-fold more reporting and heart rate very 5 seconds) and introduction of a Readiness score tells us that consumers have bought into these metrics and they are joining the club. However, all of this is occurring with a backdrop of tens millions of users, claims about the data that are not backed up by adequate evidence, marketing way out in front of whatever limited data exists, and not being transparent about their readiness score algorithms. The companies can well afford to do the research that is needed to connect these metrics with health outcomes show, once and for all, that increasing HRV or using readiness scores promotes our health. If they believed and invested in the products they are selling, we’d not be in this position of not knowing. That’s essentially where we are with HRV and readiness scores. Perhaps someday this will change and we’ll have good reason to embrace them.
NB: I wrote this post. No AI. I have no conflicts of interest with any of its content.
Ground Truths has 215,000 subscribers from every US state and 214 countries. There are over 300,000 followers of Ground Truths so more than 90,000 folks who can easily convert to be free subscribers.
Your subscription to these free essays and podcasts makes my work in putting them together worthwhile. If you’re not a subscriber, please join!
If you found this interesting PLEASE share it!
Share Ground Truths
The proceeds from all voluntary paid subscriptions go to support our summer internship program. It enabled us to accept and support a record number of 62 summer interns that joined us in 2026! These are high school, college and medical students selected from thousands of applicants. We couldn’t do this expanded program without the funds coming in through Ground Truths. Thank you!